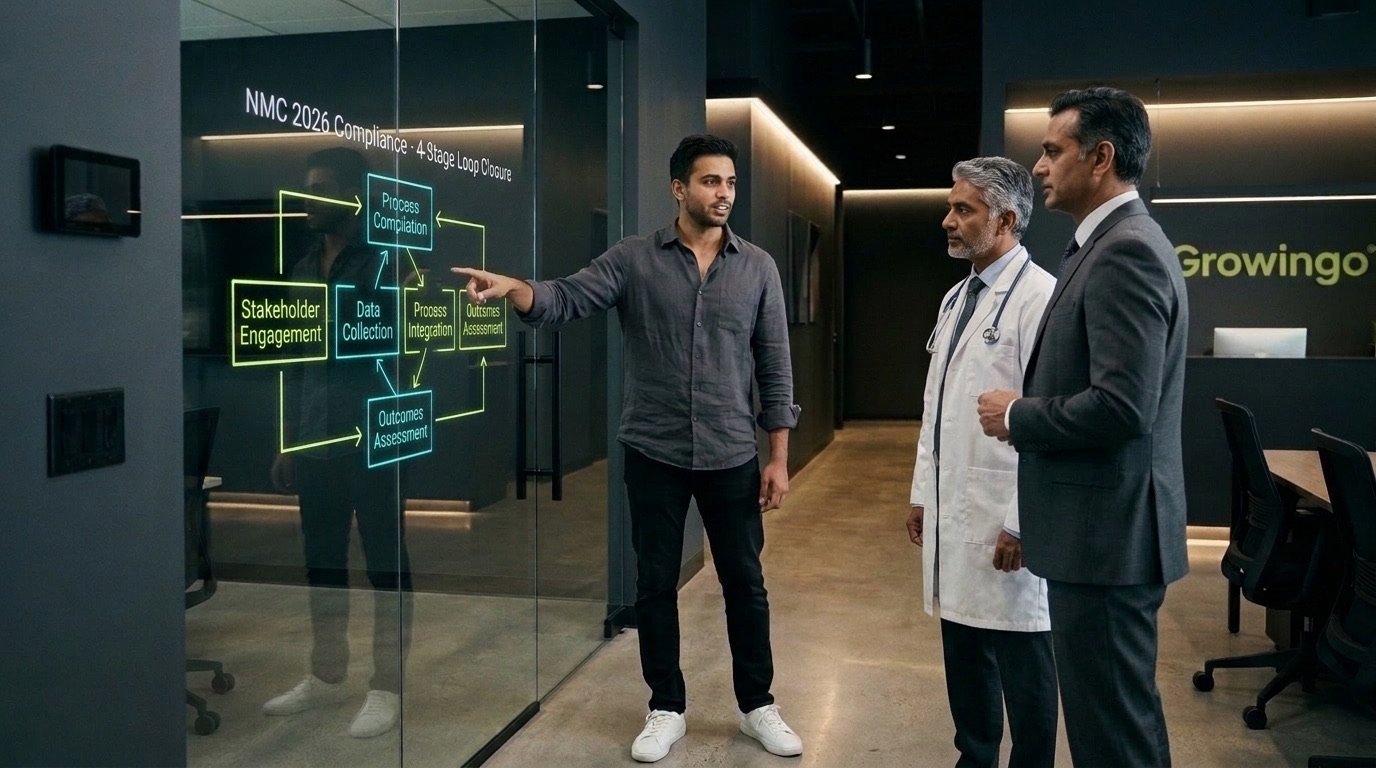
Worried that the 6 October 2026 NMC advertising guidelines just killed your hospital's patient pipeline? Take a breath. They didn't kill hospital growth. They killed lazy agency shortcuts—and that's exactly why we built Growingo.
On 6 October 2026, the National Medical Commission's Ethics and Medical Registration Board issued its Guidelines on Ethical Advertising and Public Communication by Hospitals, Medical Institutions, and Registered Medical Practitioners. They came into force that same day. There's no transition window. It's immediate.
Read the prohibited list slowly. Patient testimonial reels. "Best cataract surgeon in Delhi" headlines. Festival discounts and free-consultation hooks. Agencies paid per lead. AI-generated promo videos. That's most of the hospital marketing running in India today. If your agency depended on those levers, their playbook died on 6 October. It's over.
Here's why Growingo partner hospitals aren't panicking. None of those banned levers ever drove durable surgical revenue. They drove cheap form fills that clogged your calling desk while your operating theatres sat half full. Growingo replaces vanity lead generation with a 4-stage closed-loop revenue engine built on factual clinical authority, D-1 attended OPD walk-in attribution (CPQL), and 6-month surgical cohort ROAS. You grow faster, and you don't breach a single NMC clause.
How Growingo Scales Your Hospital Inside the October 2026 NMC Rules
- The guidelines treat search, social, sponsored, influencer, and AI-generated promotion as advertising under Clause 3.2. Hiring a conventional agency doesn't move the liability off your hospital or your doctors.
- Testimonials, before-after images, superlatives, discount hooks, fear ads, and per-patient agency payouts are barred. Patient consent doesn't rescue any of them.
- Growingo builds surgical demand from what Clauses 8.2(iii), 8.3(i), and 9.1 explicitly protect: factual institutional capabilities, transparent fee schedules, doctor directories with SMR/NMR registration numbers, and clinician-led education.
- Measurement isn't advertising. Growingo's D-1 HMIS reconciliation tracks cost per attended OPD visit (CPQL) and 6-month cohort surgical revenue so your board sees real ROAS instead of vanity CPL.
- Growingo operates on transparent scope-based retainers steered by CPQL and ROAS telemetry—never the per-patient commissions now outlawed under Clause 8.1(viii).

What the 6 October Guidelines Actually Changed
The 2002 Professional Conduct Regulations already barred doctors from self-promotion. What's new is precision. The guidelines name the channels, name the tactics, and pull hospitals under the same standard as individual doctors. Eleven clauses reshape every hospital marketing plan in India.
| Practice | Where It Stands Now | Clause |
|---|---|---|
| Digital, search, sponsored, influencer & AI promotion | Counts as advertising when promotional | 3.2 |
| Content published by an agency or influencer | Hospital or doctor stays responsible | 4.4 |
| Patient testimonials, reviews, endorsements for promotion | 3.2 Expl. V, 6.2, 8.1(xi) |
|
| Before-after photos, surgical results, success stories | 8.1(v) |
|
| "Best", "No.1", "leading", "top", "most trusted" | Only if independently verifiable, methodology disclosed | 8.1(ix) |
| Discounts, coupons, cashbacks, free procedures | 8.1(x) |
|
| Fear-based or demand-creating ads | 8.1(i) |
|
| Commissions, referral fees, per-patient agency contracts | 8.1(vii), 8.1(viii) |
|
| Bought followers, fake reviews, algorithm manipulation | 8.1(xii) |
|
| AI-generated promotional campaigns, AI patient images | 7.2 |
|
| Hospital ads that promote an individual doctor | 8.3(ii) |
What's still open is wider than most hospitals assume. Institutions can publish their name, location, departments, facilities, diagnostic equipment, emergency services, accreditation, and charges under Clauses 8.3(i) and 9.1 without restriction. A website doctor directory with qualifications and registration details counts as patient information, not promotion, under Clause 9.1, so it's safe to publish. Doctors can teach on electronic media in their own name and designation under Clause 8.2(iii), when they disclose their name, qualifications, and SMR or NMR number on every post under Clause 3.2 Explanation III.
State councils enforce a graded penalty ladder. State Medical Councils can move from a warning to removing a doctor from the register for one to three years under Clause 10.1. Hospitals answer under the Clinical Establishments Act or the state equivalent. Don't ignore it.
Why Your Current Agency's Playbook Just Broke
Walk through a typical hospital lead-generation stack. An instant-form campaign launches with a "Free LASIK consultation this week" hook. A patient video says the surgery changed her life. A headline calls the lead surgeon the city's best. An agency invoices per lead, sometimes per OPD booking.
Under the new guidelines, every component of that stack is now a breach. It won't survive scrutiny. The offer hook fails Clause 8.1(x). The patient video fails Clause 8.1(xi). The superlative fails Clauses 8.1(ix) and 8.3(ii). The per-lead invoice fails Clause 8.1(viii).

We've written before about why hospital agencies optimise for CPL instead of revenue, and this broken stack shows that problem in its purest form. Discounts and testimonials pull people who click easily, not people with a surgical decision forming. CPL falls. Attended consultation rates fall right along with it.
So the hospitals that'll feel 6 October hardest aren't the ones doing the most marketing. They're the ones whose agency chased raw lead volume. Those agencies built their pipeline on the cheapest inputs available, and the NMC just banned those inputs. They can't run them anymore.
The hospitals working with Growingo barely flinched. We already measured past the form fill. We're ready.
"The tactics the NMC banned on 6 October—festival discounts, free OPD hooks, patient testimonial reels, and per-lead agency contracts—never built surgical volume. They built call-centre fatigue. When Growingo connects your brand positioning to D-1 attended OPD walk-ins (CPQL) and 6-month cohort revenue, regulatory compliance and profitable hospital growth point in the exact same direction."
The Growingo Solution: 4 Stages Built for NMC-Compliant Scale
Growingo's methodology runs in four connected stages. Each stage sits squarely on the permitted side of the October 2026 rules because each optimises for verified HMIS surgical revenue rather than cheap form volume.

01 · Diagnosis: Find Out What Your Revenue Actually Depends On
Before a rupee moves, Growingo inventories every channel carrying your hospital's or a doctor's name across your website, Google Business Profile, Meta and Google accounts, YouTube, WhatsApp broadcasts, and listing platforms. We check each live asset against the eleven clauses above. Then we trace your Akhil or KareXpert HIS logs to map which share of current OPD volume comes from now-barred tactics. That number is your real exposure, and most boards haven't seen it.
02 · Brand Foundation: Build Trust From Facts the Guidelines Protect
Discounts manufacture urgency. Brand Foundation builds preference, and preference survives a regulation change. The guidelines leave a hospital free to show departments, surgical technology, accreditation, published charges, and a full doctor directory. Those are the exact proof points a considered-purchase patient weighs over weeks. Growingo turns them into a coherent institutional story so you don't rely on a stack of offers.
03 · Growth Execution: Campaigns That Inform, Never Solicit
In Growth Execution, Growingo's search ads follow one formula combining department, location, a verifiable fact, and a "Learn more" action. "Cataract & Retina Department, Dwarka · Charges Listed Online" replaces "Best Eye Surgeon, 50% Off". Meta runs clinician-led explainers from the hospital page, with registration details on screen so patients aren't misled. SEO content answers the questions patients actually type into Google and AI search, without superlatives. Any AI-assisted asset gets human medical review and a source mark under Clause 7.2.
04 · Loop Closure: Measurement Is Not Advertising
Loop Closure is the stage the guidelines don't touch, and it's the one that decides whether compliant marketing stays funded. Growingo's D-1 reporting reconciles yesterday's attended OPD visits (CPQL) to campaign source before 08:30 AM every morning. A 6-month forward cohort then matches surgical billing back to the inquiry that started it, so your finance team isn't guessing.
Without that loop, a hospital that drops its offer hooks sees CPL rise and panics. With Growingo's loop closure, the board sees what actually happened. You'll get fewer junk leads, more attended consultations, and steady or rising surgical revenue per rupee.
We build one caution in by default. Feeding OPD outcomes back to ad platforms must run on documented consent, SHA-256 hashed identifiers, and non-clinical event names, so there's no diagnosis or procedure in the payload. Clause 7.6 ties digital use of patient data to the DPDP Act 2023, and we treat that as a design constraint, not an afterthought.
The proof this works isn't theoretical; it's the founding case behind Growingo. At an eye hospital chain, closing the loop from impression to OPD to IPD revenue let paid digital spend scale over 150% while ROAS rose from 1.9x to 4.0x (read the eye hospital case study). The lever was measurement and brand, not cheaper leads. That's durable growth.
Read Your Agency Contract Before Your Ad Copy
Most compliance checklists start with creative. Don't start there. Start with the contract instead.
Clause 8.1(vii) bars commissions, referral fees, and lead-generation fees linked to procuring patients. Clause 8.1(viii) says agency, influencer, and platform arrangements mustn't pay per patient procured or referred. A cost-per-lead or cost-per-booking agency deal now sits directly against that text, and Clause 4.4 means the hospital can't point at the agency when regulators question a campaign.
There's a commercial argument here too, separate from the legal one. An agency paid per lead works to maximise lead count. That incentive is what produced the offer hooks and testimonial reels in the first place. It wears out your calling desk. You don't want that.
Growingo's fees are retainer and project-based. We report cost per attended OPD visit (CPQL) and cohort ROAS to steer budget decisions. We never invoice against leads, patients, or surgeries. The metric guides the media spend; it isn't the billing unit.
Growingo's Eight-Point Gate Before Any Asset Goes Live
We run this gate on every ad, post, landing page, and video. It takes minutes per asset and removes the guesswork for your marketing team, so you're never caught off guard.

Source Account
We confirm the asset publishes from the hospital's own account, and isn't a doctor's personal promotion under Clause 8.3(i).
Claims & Superlatives
Did someone write "best", "top", "No.1", "painless", "guaranteed", or an unverified success rate? We remove it, or attach the independent methodology so you don't breach Clause 8.1(ix).
Zero Inducements
Does the copy push a discount, free consultation, cashback, or limited-time offer? We replace it with factual published charges under Clause 8.1(x) so it's compliant.
Patient Privacy
Does the creative show a testimonial, before-after photo, recovery story, or identifiable patient face? We remove it because patient consent doesn't exempt Clauses 6.2, 8.1(v), and 8.1(xi).
Doctor SMR/NMR ID
Does the asset name a doctor? We show their name, qualifications, registration status, and SMR or NMR number—informing patients so we don't glorify the clinician.
Non-Alarmist Tone
Does the message create fear or unnecessary demand for a diagnostic test or surgical procedure? We cut alarmist hooks under Clause 8.1(i) so patients aren't pressured.
AI Source Mark
Did the team use AI tools? We complete human medical review, add a visible source mark, and verify there aren't any synthetic patients under Clause 7.2.
Approval Audit Log
We record who wrote the asset, who approved it, and when it went live. That dated record protects your hospital board so you've got proof ready.
The log matters more than it looks. When a State Medical Council issues a show-cause notice, a dated approval trail is your hospital's first line of defence. Don't publish without it.
Frequently Asked Boardroom Questions
Can hospitals still run Google and Meta ads under the 2026 NMC guidelines?
Yes, they can. Hospitals may advertise factual, verifiable information including departments, facilities, services, accreditation, and charges under Clauses 8.3 and 9.1. The ads mustn't use superlatives, outcome guarantees, offers, or promotional portrayal of individual doctors.
Our agency is paid per lead. Is that now a problem?
It's a risk worth fixing quickly. Clause 8.1(viii) bars agency arrangements that pay per patient procured or referred, and Clause 8.1(vii) covers lead-generation fees linked to procuring patients. Moving to Growingo's scope-based retainer removes the exposure and the incentive behind lead-volume tactics so you're protected.
Will CPL go up if we drop offers and testimonials?
Often, yes, in the first few weeks. That's why Growingo's loop-closure measurement matters. If attended OPD visits and cohort surgical revenue hold or rise, the higher CPL is buying better patients, and the board can see it. You won't panic over vanity CPL.
Can our doctors still post on Instagram and YouTube?
Yes, for education in their own name and designation under Clause 8.2(iii), when they disclose their name, qualifications, registration status, and SMR or NMR number. They can't post to promote their practice, and they mustn't use patient testimonials.
Do old posts published before 6 October count?
The guidelines took effect immediately and didn't set a grace period. The prudent course is auditing and cleaning legacy posts, pinned content, and ad libraries now so you don't leave old violations live.
STATUTORY DISCLAIMER & PRIMARY REGULATORY SOURCES
Disclaimer: Growingo is a healthcare growth and marketing firm, not a law firm. This article reflects our reading of the NMC public notice dated 6 October 2026 and is general information, not legal advice. Read the official notice and consult a healthcare lawyer before acting.
- NMC Guidelines on Ethical Advertising and Public Communication, Public Notice 6 Oct 2026
- National Medical Commission (NMC) Official What's New Portal
- Medical Dialogues: NMC bars celebrity, influencer and patient testimonials & promotional use of doctors' photographs
- BestMediaInfo: NMC issues ethical advertising guidelines for doctors and hospitals
Worried About Your Exposure? Find Out How Much OPD Volume Depends on Banned NMC Tactics
In a 45-minute diagnosis, Ashish Jha maps your live campaigns against the October 2026 guidelines, then traces which share of attended consultations comes from compliant channels. You leave knowing your exposure and the Growingo closed-loop path to replace it. No sales reps, no slides.